
Archive

Tag Archives: wellness

Healthcare assistants play an essential role in administering medicines in residential care. But safe administration is not the same as clinical oversight. Unless the system ensures that residents’ medicines are regularly reviewed, interactions are identified, adverse effects are investigated and professional advice is readily available, preventable harm can go unnoticed.

The distinction that matters

In care homes across the UK, medicines are frequently administered by healthcare assistants and other care staff who are not registered healthcare professionals. This arrangement is not inherently unsafe or inappropriate. Staff who have received suitable training, been assessed as competent and are working within clear procedures can administer prescribed medicines safely and effectively.

The problem arises when the delegation of administration is not matched by effective clinical oversight.

Giving a tablet according to a medication administration record is a different task from determining whether that tablet remains appropriate for a particular resident, whether it interacts with other prescribed medicines, or whether the resident is experiencing an adverse reaction. These activities require different knowledge, skills and professional responsibilities.

The fundamental question is not who physically gives the medicine, but who takes responsibility for ensuring that the complete medication regimen remains clinically appropriate and safe.

In a care system where GPs prescribe, pharmacies dispense and care assistants administer, responsibility can become fragmented. Each participant may perform their assigned task, yet gaps can remain between prescribing decisions, the administration of medicines, clinical monitoring and subsequent review.

For residents who are frail, living with dementia or taking multiple medicines, those gaps matter. They can mean that a harmful combination persists, a side effect goes unrecognised or an unnecessary medicine continues long after its original purpose has disappeared.

The answer is not to diminish the role of care assistants or insist that every routine dose must be administered by a nurse. It is to establish a system in which delegated administration is supported by clear accountability, accessible clinical expertise and reliable review of the resident’s treatment.

The evidence of medication errors

The risks associated with medicines management in care homes have been documented in published research for many years.

In 2009, Barber and colleagues published the Care Homes’ Use of Medicines Study (CHUMS), investigating medication errors among residents in UK care homes. The study examined 256 residents across 55 homes and found that 178 residents, or 69.5% of the sample, had experienced at least one medication error. Residents were taking an average of eight medicines.

The researchers identified contributing factors that included staff workload, interruptions during medication rounds, inadequate training, inaccurate records and communication failures between care homes, GP practices and pharmacies. They also highlighted weaknesses in overall responsibility for medicines safety.

These findings are important because they point beyond individual mistakes. A medication error may occur at the point of administration, but its underlying causes can lie elsewhere: an inaccurate prescription, a failure to communicate a change in treatment, inadequate monitoring or the absence of an effective process for reviewing the whole medication regimen.

Barber et al., Care Homes’ Use of Medicines Study, Quality and Safety in Health Care, 2009.

The figures must be interpreted in their historical context. They describe the residents and homes studied in 2009 and should not be presented as an estimate of the current national error rate. Nevertheless, the study remains an important examination of the organisational weaknesses that can undermine medicines safety.

A 2022 review published in The Pharmaceutical Journal, examining medication errors and inappropriate medicine use in UK care homes, also identified prescribing and administration errors as significant concerns. The literature discussed factors including polypharmacy, understaffing, dementia, swallowing difficulties and inadequate communication between prescribers, pharmacists and care staff. The authors highlighted the potential value of regular pharmacist-led medication reviews, staff education and improved reporting of medication errors.

Pepple and Boumechache, Errors and the inappropriate use of medicines in UK care homes, 2022.

Taken together, these publications support a clear conclusion: medicines safety depends on the reliability of the whole system, not simply on whether the person administering a dose follows the correct procedure.

Why correct administration does not guarantee safe treatment

Imagine a resident receiving medicines for hypertension, heart disease, diabetes, chronic pain and anxiety. Each medicine may have been prescribed for a legitimate reason. The resident’s care assistant administers each dose correctly and records it accurately.

Yet the resident begins to experience dizziness, increasing confusion and recurrent falls.

The administration records may reveal no error. The medicines may have been given at the prescribed times and in the prescribed doses. Nevertheless, the combined treatment may be contributing to the resident’s deterioration.

Several medicines can have additive effects on blood pressure, alertness or balance. Changes in kidney function can affect the handling of particular drugs. An illness, an episode of dehydration or a hospital admission can alter the balance between the benefits and risks of an established regimen. A medicine that was once appropriate may become unnecessary or harmful as the resident’s condition changes.

A care assistant may be the first person to notice that the resident is unusually drowsy or unsteady. That observation is clinically valuable and should trigger an appropriate response. But determining whether the symptoms represent an adverse drug reaction, an interaction, an excessive cumulative effect or an unrelated illness requires further assessment.

This is where the distinction between administration and oversight becomes critical.

Care assistants should not be expected to diagnose complex drug interactions or independently alter prescriptions. Equally, a system should not depend on them recognising every potential interaction or adverse effect before a qualified professional becomes involved.

Their responsibility is to administer medicines within their competence, observe the resident, document relevant information and escalate concerns. The clinical system must then ensure that those concerns can be assessed promptly and that treatment can be reconsidered when necessary.

Without this link, even a perfectly completed medication administration record can coexist with unsafe treatment.

Polypharmacy requires active clinical management

Polypharmacy is common among older people and is not automatically inappropriate. For residents with several chronic conditions, multiple medicines may be necessary to manage symptoms, prevent complications and maintain quality of life.

The problem is inappropriate or insufficiently reviewed polypharmacy: combinations that no longer provide sufficient benefit, create avoidable risks or continue without adequate consideration of the resident’s changing circumstances.

Potential concerns include:

  1. Interactions that increase the toxicity of one or more medicines.
  2. Combined sedative effects that contribute to falls, impaired alertness or confusion.
  3. Multiple medicines contributing to low blood pressure or an increased risk of bleeding.
  4. Adverse effects being mistaken for the progression of dementia or another underlying illness.
  5. Medicines continuing after their original indication has disappeared.
  6. A new medicine being prescribed to treat a symptom caused by another medicine, creating a prescribing cascade.

Identifying these problems requires more than checking the individual entries on a medication administration record. It requires consideration of the resident’s complete treatment, medical history, current symptoms, relevant investigations and personal priorities.

The Royal Pharmaceutical Society’s report, The Right Medicine: Improving Care in Care Homes (2016), provides a professional basis for strengthening this approach. It advocates a greater role for pharmacists in improving medicines management and working with care homes and other healthcare professionals.

Royal Pharmaceutical Society, The Right Medicine: Improving Care in Care Homes.

The significance of this approach is that clinical oversight should examine the whole regimen, rather than treating each prescription as an isolated decision. It should also establish whether intended benefits are being achieved, whether adverse effects are emerging and whether any medicines can be reduced or discontinued safely.

The guidance exists. The challenge is making it effective.

The National Institute for Health and Care Excellence (NICE) published Managing medicines in care homes (SC1) in 2014. Its recommendations address medicines-related responsibilities, staff competence, record keeping, medication errors, communication and medication reviews.

NICE expects care home providers to ensure that staff administering medicines are suitably trained and assessed as competent. It also recommends arrangements for medication reviews, including the involvement of a named health professional with appropriate clinical experience and knowledge of the resident. Reviews should take account of the resident’s needs and preferences and involve other professionals when appropriate.

Source: NICE, Managing medicines in care homes, recommendations.

These recommendations support the distinction at the heart of this article. Care staff can undertake the practical task of administering medicines, but this must operate within a wider framework of professional review, monitoring and accountability.

The existence of guidance does not establish that all homes follow it effectively. Nor does it prove that every home without an on-site registered nurse is unsafe. The relevant issue is whether each resident has access to appropriate clinical oversight, whether responsibilities are clearly assigned and whether the system responds effectively when risks emerge.

A written medicines policy is not enough if staff cannot obtain timely advice. A completed training record is not enough if nobody reviews the consequences of a complex medication regimen. A periodic medication review is not enough if significant changes in a resident’s condition are not recognised and acted upon between reviews.

The test should be whether the arrangements work in practice.

Why periodic reviews must be supported by ongoing oversight

Scheduled medication reviews are important, but they cannot anticipate every change in a resident’s health.

A hospital discharge may introduce new medicines, discontinue existing treatments or alter doses. An acute illness may affect kidney function, hydration or the resident’s ability to swallow. A new symptom may indicate an adverse reaction. A fall or a sudden change in mental state may require an urgent reassessment of treatment.

Care staff are often best placed to observe these changes because they provide day-to-day support. Their observations should feed into a clear clinical escalation process.

This does not mean that a doctor or pharmacist must be physically present whenever medicines are administered. Nor does it mean that every dose requires fresh clinical authorisation. It means that suitably qualified professionals must be responsible for reviewing treatment, be able to access relevant information and be available to advise when circumstances require reassessment.

NHS England’s structured medication review programme identifies care home residents as a group for whom structured reviews may be particularly important. The purpose is to consider the benefits and risks of treatment, particularly in people with complex or problematic polypharmacy.

NHS England, Structured medication reviews and medicines optimisation.

The policy direction is clear: medicines should be reviewed in the context of the individual resident, rather than continued indefinitely simply because they remain on a repeat prescription.

What is needed is a dependable connection between these reviews and everyday care. Staff must know how to report concerns, who will assess them and how resulting decisions will be communicated and implemented.

A model that separates responsibilities but joins up care

A safer approach would preserve the contribution of healthcare assistants while strengthening the clinical systems that support them.

1. Clear responsibility for the complete medication regimen

Every resident should have an identifiable arrangement for clinical medication review. Depending on the resident’s needs and local services, this may involve a suitably qualified pharmacist, GP or other appropriately trained prescriber.

The important requirement is that responsibilities are explicit, relevant information is available and someone has the authority and competence to assess the complete regimen.

Naming a professional on a care plan is not sufficient if that person cannot obtain the information needed to conduct a review or if recommendations are not followed through.

2. Comprehensive, risk-based medication reviews

Reviews should consider the indication for each medicine, potential interactions, cumulative side effects, relevant monitoring, the resident’s response to treatment and the possibility of reducing unnecessary medication.

They should also take account of the resident’s wishes and priorities. The objective is not to minimise the number of medicines at any cost, but to achieve the best balance of benefit and harm for the individual.

3. Timely clinical advice when concerns arise

Care staff need clear instructions on what to do when a resident develops new symptoms, refuses medicines, experiences a fall or shows a significant change in their condition.

There must be an effective route to professional assessment, with urgent concerns escalated appropriately. Where a medication discrepancy or possible adverse reaction is identified, staff need to know whom to contact and how the outcome will be recorded.

4. Training appropriate to the responsibilities of care staff

Training should cover safe administration, accurate documentation, the importance of following the current prescription and the recognition of warning signs. Staff should know the limits of their role and be confident about reporting concerns without being expected to make clinical decisions outside their competence.

Competence assessments and refresher training are necessary, but training should complement rather than substitute for professional oversight.

5. Monitoring and learning from medication incidents

Providers and their clinical partners should monitor errors, omissions, discrepancies, adverse reactions and delays in medication review. Near misses should also be reported and examined.

When incidents occur, investigations should consider not only the actions of the person administering the medicine but also the prescribing process, communication between organisations, staffing conditions, access to clinical advice and the adequacy of monitoring.

The objective should be to correct weaknesses in the system rather than reflexively attributing every failure to an individual member of staff.

6. Properly resourced clinical involvement

Pharmacist input, GP support and nursing expertise require time, agreed responsibilities and effective communication. Providers and commissioners must make suitable arrangements rather than relying on informal assistance or the goodwill of already overstretched professionals.

The appropriate level of involvement will vary with residents’ needs and the complexity of their treatment. However, the need for clinical oversight should not depend on whether a home happens to have a registered nurse permanently on site.

These changes would not remove all medication errors. They would, however, address the organisational conditions that can allow prescribing problems, adverse effects and medication discrepancies to persist undetected.

Accountability must extend beyond the person administering the medicine

When a medication error occurs, the most visible event may be an incorrect dose, an omitted tablet or a missing signature on a medication administration record.

Those matters require investigation. But a complete investigation must also ask whether the prescription was appropriate, whether the records were accurate, whether changes in treatment were communicated, whether monitoring was undertaken and whether staff could obtain clinical advice when necessary.

A care assistant may be responsible for following the procedures and instructions applicable to their role. They should not, however, become the default point of accountability for weaknesses that originate elsewhere in the system.

Responsibility must follow professional roles and actual control over decisions.

Prescribers are responsible for their prescribing decisions. Pharmacists contribute medicines expertise. Registered nurses, where involved, have responsibilities appropriate to their roles. Care assistants must work within their competence and report concerns. Care providers must maintain safe systems and ensure staff have the necessary training, information and support. Commissioners and healthcare services must establish workable arrangements for clinical input.

The Care Quality Commission’s medicines-management guidance reinforces the importance of safe systems for prescribing, handling and administering medicines.

CQC, guidance on medicines management and learning from safety incidents.

The central principle is straightforward: a system should not rely on every individual performing their task perfectly to compensate for gaps in the organisation of care. It should include safeguards that can identify problems, escalate concerns and correct mistakes before they cause harm.

The resident must remain at the centre

Medication safety is not simply a matter of compliance with procedures. It is about protecting people whose health, independence and quality of life may be profoundly affected by the medicines they receive.

A resident living with dementia may be unable to describe dizziness, nausea or increasing confusion. Someone with swallowing difficulties may struggle to take medicines as prescribed. A frail resident taking several medicines may be unable to recognise that increasing tiredness or unsteadiness could be treatment-related.

These people depend on care staff to notice changes and on clinical professionals to interpret those observations and act appropriately.

They also deserve to be involved in decisions about their treatment to the extent that they are able, with appropriate support where needed. A medication review should not be a purely administrative exercise between professionals. It should consider what matters to the resident, which symptoms are troubling them and whether the treatment continues to serve their interests.

Effective oversight therefore protects not only against medication errors but also against unnecessary treatment, avoidable side effects and the continuation of medicines that no longer provide sufficient benefit.

Conclusion: strengthen oversight, not blame care assistants

The evidence from UK care home research, together with guidance from NICE, the Royal Pharmaceutical Society and NHS England, supports the need for better-organised medicines management, clear professional responsibilities and structured clinical review.

The solution is not to prohibit appropriately trained healthcare assistants from administering medicines. Delegated administration can be a legitimate and effective part of residential care. The solution is to ensure that delegation never becomes a substitute for clinical oversight.

Administering a medicine correctly does not establish that the medicine is appropriate, that its combination with other treatments is safe or that its effects are being monitored adequately.

Every care home should be able to explain who is responsible for reviewing each resident’s medication regimen, how potentially harmful interactions and adverse effects are identified, how changes in the resident’s condition trigger reassessment and how quickly qualified clinical advice can be obtained.

It should also be possible to demonstrate that medication reviews lead to action, that incidents are investigated and that recurring problems result in improvements to the system.

If these safeguards are absent or ineffective, the problem is not simply a lack of individual training. It is a failure to connect the administration of medicines with the clinical expertise required to manage their risks.

Healthcare assistants should be supported to carry out their responsibilities safely and confidently. Residents, meanwhile, should be entitled to expect that the medicines they receive are not only administered correctly but also prescribed appropriately, reviewed regularly and monitored with the seriousness their health requires.

The objective must be a system in which responsibility for administering medicines is delegated appropriately, but responsibility for clinical oversight is never left ambiguous.

Principal references

  1. Barber, N. et al. (2009). Care Homes’ Use of Medicines Study (CHUMS). Full paper .
  2. Pepple and Boumechache (2022). Errors and the inappropriate use of medicinesin UK care homes. The Pharmaceutical Journal .
  3. Royal Pharmaceutical Society (2016). The Right Medicine: Improving Carein Care Homes. Report .
  4. NICE (2014). Managing medicines in care homes (SC1). Recommendations .
  5. NHS England. Structured medication reviews and medicines optimisation. Programme guidance .
  6. Care Quality Commission. Medicines management: learning from safetyincidents. Guidance .

Editorial note: The article is framed primarily around England because the cited NICE and CQC guidance applies there. Before publication as a UK-wide policy critique, the regulatory position and equivalent guidance in Scotland, Wales and Northern Ireland should be checked separately. The research statistics are attributed to the original studies rather than presented as current national estimates.
Psychiatric diagnoses are often made from patterns of symptoms, behaviour, history and clinical observation. Those tools are important—but when a diagnosis is questionable, atypical, unusually severe, treatment-resistant or accompanied by cognitive or neurological changes, they should not necessarily be the end of the investigation.

A questionable psychiatric diagnosis should trigger a serious search for neurological, cognitive, metabolic and endocrine explanations.

This is not an argument that psychiatric illness is “not real,” nor that every person with depression, psychosis, bipolar disorder or another psychiatric condition needs an enormous battery of tests. It is an argument for diagnostic humility: before permanently attributing unexplained changes in behaviour, personality, cognition or perception to a psychiatric disorder, clinicians should ask whether the brain and the body’s underlying physiology have been adequately investigated.

Start with objective cognitive testing

A detailed neuropsychological or neurological cognitive assessment can provide information that a conventional psychiatric interview may miss.

Memory, attention, processing speed, language, executive functioning, visuospatial abilities and working memory can be measured systematically. Patterns of impairment may point toward neurological disease, acquired brain injury, neurodegenerative processes or other conditions that can present with apparently psychiatric symptoms.

This is particularly important when someone reports a significant change from their previous cognitive functioning. The question should not simply be, “Does this person meet the criteria for a psychiatric disorder?” It should also be, “What has happened to this person’s brain function?”

Modern neuropsychiatric assessment explicitly recognises the importance of cognitive, neurological and laboratory information in understanding difficult presentations. 

MRI should not be dismissed when the presentation is unusual

When there is a credible possibility of neurological disease or brain injury, high-quality brain MRI deserves consideration.

MRI is generally more informative than CT for many structural brain abnormalities and provides better visualisation of grey and white matter and certain deeper brain structures. Neuropsychiatric references identify circumstances such as new-onset psychosis, cognitive decline, new personality change, seizures, traumatic brain injury and treatment-refractory presentations as situations in which structural imaging may warrant consideration.

The point is not that an MRI will automatically reveal the cause. It often will not. Nor should the phrase “high-resolution MRI” become a promise that subtle psychiatric symptoms can be explained by a scan.

The point is simpler: if neurological damage or disease is genuinely in the differential diagnosis, it should be investigated rather than assumed away. NICE material on first-episode psychosis likewise recognises neurological examination and targeted laboratory and EEG investigation, with MRI or CT considered when an organic cause is suspected.

EEG deserves consideration when electrical brain dysfunction is plausible

Some neurological disorders can produce behavioural, perceptual or cognitive symptoms that can be mistaken for psychiatric illness.

Seizure disorders are an obvious example. EEG is particularly relevant where there are episodes that are sudden, stereotyped, episodic or otherwise suggestive of abnormal electrical activity. Psychiatric assessment guidance notes that continuous or ambulatory EEG can sometimes be necessary to document abnormal activity when ordinary testing does not capture an event. 

That is why, where the clinical history makes intermittent electrical dysfunction plausible, a normal short routine EEG should not automatically end the neurological investigation.

In selected cases, prolonged ambulatory or video EEG, including a 48-hour study where clinically justified may provide substantially more opportunity to capture abnormalities than a brief recording.

But this distinction matters: a 48-hour EEG should be clinically indicated, not imposed indiscriminately on every psychiatric patient. Current psychiatric guidance generally describes EEG as an investigation to use when neurological history or examination raises the possibility of a seizure disorder or other neurological process. 

Endocrine and metabolic causes should be taken seriously

The brain does not operate independently of the rest of the body.

Thyroid dysfunction, metabolic abnormalities and other systemic illnesses can produce changes in mood, cognition, energy, sleep, behaviour and mental state. Consequently, laboratory investigation belongs in the differential diagnosis of unexplained psychiatric and cognitive presentations.

There is already recognition within psychiatric practice that physical and laboratory assessment is an important component of diagnosis and management. Standard investigations can include thyroid function and metabolic testing, with additional testing guided by the individual’s presentation. The principle should therefore be:

Do not diagnose the mind while ignoring the body.

Where symptoms suggest an endocrine disorder, the appropriate endocrine investigation should be pursued rather than assuming that psychiatric symptoms are necessarily primary.

This is not “psychiatry versus neurology”

The false choice is between saying that somebody has a psychiatric illness and saying that they have a neurological illness. Sometimes the answer is both. Sometimes neither initial diagnosis is correct.

A person can have a psychiatric disorder and a neurological disorder. Brain injury can coexist with depression. Epilepsy can coexist with anxiety. Endocrine disease can produce psychiatric symptoms. Medication, substances, sleep disorders and systemic illness can complicate an otherwise genuine psychiatric condition.

Neuropsychiatry exists precisely because the boundary between neurological and psychiatric presentations is not as clean as diagnostic labels can sometimes imply. The professional literature explicitly advocates an integrated approach rather than a rigid division between “psychiatric” and “neurological” disease.

The standard should be diagnostic confidence—not diagnostic convenience

The strongest case is not for testing everyone. It is for testing appropriately when the diagnosis does not adequately explain the person in front of you.

Red flags might include:

  • a sudden or unusually late onset of psychiatric symptoms;
  • substantial or unexplained cognitive decline;
  • new personality or behavioural change;
  • episodes suggesting seizures or altered consciousness;
  • focal neurological symptoms or abnormal neurological findings;
  • a history of significant head injury;
  • an unusually atypical clinical presentation;
  • rapid deterioration;
  • unexpected treatment resistance; or
  • a substantial discrepancy between the psychiatric diagnosis and the person’s observed cognitive or neurological functioning.

These are precisely the sorts of circumstances in which psychiatric literature recommends considering additional medical or neurological evaluation. 

A more rigorous standard

When a psychiatric diagnosis is questionable, the appropriate response should not be to simply repeat the same psychiatric assessment until the original diagnosis appears more convincing.

It should be to expand the differential diagnosis. That may mean comprehensive cognitive testing, neurological examination, appropriate blood and endocrine investigations, high-quality brain MRI, and, when the history warrants it prolonged EEG monitoring such as a 48-hour ambulatory study.

None of these tests is infallible. None should be treated as a magical machine capable of proving or disproving a psychiatric diagnosis. And indiscriminate testing can create false positives, unnecessary anxiety and inappropriate treatment.

But the opposite error can be far more consequential: mistaking an unexplained neurological, cognitive or physiological disorder for a purely psychiatric one and never looking for anything else.

A psychiatric label should be a clinical hypothesis supported by evidence—not a reason to stop investigating.

When the diagnosis is questionable, the brain deserves to be examined, cognition deserves to be measured, electrical activity deserves to be considered, and the body’s physiology deserves to be investigated.

Good psychiatry should not fear neurological investigation. It should demand it when the clinical picture warrants it.

This is a drug well known to us for terrible adverse reactions – severe restlessness and Akathisia, not to mention excessive expenditure on shopping.. Once again it is prescribed off- label to counteract the effects of hyperprolactinaemia caused by another, despite substantial physical health decline and metabolic issues. This drug should not be accepted as any substitute for essential pathophysiological referrals and tests when there is overwhelming evidence in terms of need. I have highlighted the very important point on appropriateness. I will also highlight applicable issues below

The use of adjunctive aripiprazole to treat antipsychotic-induced hyperprolactinaemia has become an increasingly accepted off-label strategy within psychiatric practice. Randomised trials and systematic reviews demonstrate that low-dose aripiprazole can reduce serum prolactin concentrations in many patients receiving prolactin-raising antipsychotics. Yet clinical efficacy alone does not determine whether prescribing is appropriate.

Where treatment is off-label, the patient remains prescribed a long-acting depot antipsychotic, and there is evidence of multiple endocrine or metabolic abnormalities, the clinician’s responsibilities extend well beyond correcting a biochemical abnormality. The decision engages principles of clinical governance, informed consent, multidisciplinary care and, ultimately, the legal standard of care.

The medico-legal question is therefore not simply whether aripiprazole lowers prolactin. It is whether introducing a second dopamine-modulating medicine represents a reasonable, proportionate and defensible clinical response in the individual patient.

Off-Label Prescribing and the GMC: Professional Responsibilities

The General Medical Council’s Good practice in prescribing and managing medicines and devices recognises that prescribing outside a medicine’s licence may be appropriate. However, the guidance also makes clear that such prescribing carries enhanced professional responsibilities.

The prescriber should be satisfied that:

  • sufficient evidence or clinical experience supports the proposed treatment;
  • licensed alternatives have been properly considered;
  • the anticipated benefits outweigh foreseeable risks;
  • the patient is informed that treatment is being used outside its licensed indication where discussion is practicable;
  • material risks and reasonable alternatives are discussed;
  • the clinical reasoning is documented; and
  • appropriate monitoring arrangements are established.

These obligations become particularly important when the additional medication is not treating the primary psychiatric illness but is instead intended to mitigate an adverse effect of another prescribed psychotropic medicine.

NICE and the Royal College of Psychiatrists: Treat the Whole Patient

NICE guidance on psychosis, schizophrenia and medicines optimisation consistently promotes careful review of antipsychotic adverse effects rather than reflexively adding further medication. Hyperprolactinaemia should prompt reassessment of the overall treatment strategy, consideration of dose reduction where feasible, or switching to a prolactin-sparing antipsychotic if clinically appropriate.

Similarly, the Royal College of Psychiatrists has repeatedly emphasised that in cases of people with severe mental illness experience disproportionate rates of obesity, diabetes, cardiovascular disease, endocrine dysfunction and premature mortality, the College advocates parity of esteem between physical and mental healthcare, requiring psychiatrists to investigate physical illness with the same rigour expected in any other medical specialty.

Persistent hyperprolactinaemia accompanied by type 2 diabetes mellitus, obesity, hypogonadism, osteoporosis or other endocrine abnormalities should therefore trigger consideration of broader endocrine pathology rather than being viewed solely as a medication side effect.

Depot Antipsychotics Create a Higher-Risk Pharmacological Environment

The addition of aripiprazole is particularly complex where the patient remains prescribed depot antipsychotic injections.

Depot preparations cannot be rapidly withdrawn if clinically significant adverse effects develop. Dopamine receptor blockade continues for weeks after administration, substantially reducing therapeutic flexibility.

If adjunctive aripiprazole precipitates akathisia, agitation, insomnia or behavioural deterioration, clinicians cannot immediately remove the underlying pharmacological interaction. Consequently, the threshold for introducing additional dopamine-modulating medication should arguably be higher than in patients treated solely with oral antipsychotics.

Akathisia Is Not a Minor Adverse Effect

Aripiprazole is generally well tolerated, but akathisia remains one of its most clinically significant adverse effects.

Patients frequently describe overwhelming inner restlessness, profound anxiety, inability to remain still, agitation and severe psychological distress. These symptoms can be mistaken for worsening psychosis, anxiety disorders or behavioural disturbance, potentially resulting in further inappropriate prescribing.

The literature has also associated severe untreated akathisia with treatment discontinuation, self-harm and suicidal ideation in some patients.

Where aripiprazole has been prescribed solely to lower prolactin concentrations, the emergence of akathisia fundamentally alters the balance between therapeutic benefit and clinical risk.

Appropriate management should include urgent clinical review, consideration of dose reduction or discontinuation, reassessment of the antipsychotic regimen, symptomatic treatment where indicated, and close follow-up until symptoms resolve.

Multiple Endocrine Abnormalities Should Prompt Endocrinology Referral

The presence of hyperprolactinaemia together with type 2 diabetes mellitus or other endocrine abnormalities should prompt clinicians to ask a broader diagnostic question.

Is the patient experiencing a medication side effect alone, or does the presentation reflect wider endocrine disease requiring specialist investigation?

Potential differential diagnoses include pituitary pathology, hypogonadism, thyroid disease, adrenal disorders, metabolic syndrome and osteoporosis.

Adding aripiprazole may improve one biochemical parameter while delaying diagnosis of another clinically significant disorder.

Referral to a consultant endocrinologist should therefore be strongly considered where endocrine dysfunction extends beyond isolated hyperprolactinaemia, where symptoms remain unexplained, or where long-term complications require specialist assessment.

The Legal Framework: From Bolam to Montgomery

The legal analysis of these prescribing decisions has evolved significantly over recent decades.

Bolam v Friern Hospital Management Committee [1957]

The Bolam principle established that a clinician is not negligent simply because another clinician would have acted differently, provided the decision accords with a responsible body of professional opinion.

Historically, this afforded considerable protection to prescribing decisions supported by accepted clinical practice.

However, modern medical negligence law has moved well beyond Bolam alone.

Bolitho v City and Hackney Health Authority [1998]

The House of Lords refined the Bolam principle by holding that professional opinion itself must withstand logical analysis.

Courts are not obliged to accept expert evidence merely because other clinicians support it. The opinion must demonstrate coherent reasoning and appropriately balance risks against benefits.

In practical terms, this means that merely stating “adjunctive aripiprazole is accepted practice” may be insufficient if inadequate consideration was given to endocrine disease, alternative treatment options, foreseeable adverse effects or the patient’s individual circumstances.

Montgomery v Lanarkshire Health Board [2015]

The Supreme Court fundamentally reshaped informed consent.

Clinicians are now under a legal duty to ensure that patients are informed of:

  • material risks associated with proposed treatment;
  • reasonable alternative treatment options; and
  • the option of declining treatment altogether where appropriate.

A risk is material if a reasonable person in the patient’s position would likely attach significance to it, or if the clinician knows, or should reasonably know that the particular patient would likely consider it significant.

Applied to adjunctive aripiprazole, this means patients should ordinarily be informed about:

  • the off-label nature of treatment;
  • the possibility of akathisia, agitation and insomnia;
  • the possibility that treatment may not adequately resolve symptoms;
  • alternatives such as dose reduction, switching antipsychotics where clinically feasible, observation, or referral for endocrine assessment;
  • the uncertainties associated with adding another psychotropic medicine.

Failure to discuss these matters may expose clinicians to criticism even where prescribing itself was pharmacologically reasonable.

Documentation: The Clinician’s Strongest Defence

In medico-legal practice, contemporaneous documentation frequently determines whether a prescribing decision can be defended.

The medical record should clearly demonstrate:

  • why adjunctive aripiprazole was preferred over alternative strategies;
  • evidence supporting off-label prescribing;
  • informed consent discussions;
  • endocrine and metabolic assessment;
  • monitoring plans;
  • review arrangements;
  • contingency planning should adverse effects emerge.

Documentation should reflect a process of clinical reasoning rather than simply recording a prescribing decision.

Conclusion

Adjunctive aripiprazole remains a legitimate therapeutic option for selected patients with antipsychotic-induced hyperprolactinaemia. However, legitimacy does not eliminate professional responsibility.

Current GMC guidance, NICE recommendations and Royal College of Psychiatrists policy all point towards careful assessment, shared decision-making, systematic physical health monitoring and multidisciplinary management.

The legal authorities of Bolam, Bolitho and Montgomery reinforce these professional duties by requiring that prescribing decisions are supported by logical clinical reasoning, informed by responsible practice, and accompanied by meaningful patient involvement.

Where a patient receiving depot antipsychotic treatment develops persistent hyperprolactinaemia alongside diabetes mellitus or other endocrine abnormalities, the question should not simply be how to suppress prolactin. The more important question is whether the patient requires comprehensive endocrine investigation before additional psychotropic medication is introduced.

In many such cases, early referral to a consultant endocrinologist, combined with a multidisciplinary review of the antipsychotic regimen, is likely to represent the most clinically robust and the most legally defensible course of action.

It is extremely concerning that this drug is viewed by some psychiatrists to be an acceptable substitute for proper referral to see a Specialist Endocrinologist, especially when this drug, tried before had adversely affected behaviour and metabolism being a poor/non metaboliser ignored. This, combined with Clopixol Depot is hardly a suitable substitute for proper referrals in relation to physical healthcare. My blog “Outdated Practices” spells the need for rigorous care in terms of treatment which is what Precision Psychiatry is all about – patients under the MH deserve the very best of care yet this is not happening in the UK. Precision Psychiatry therefore needs to be mandatory to ensure that when a patient is not responding to treatment and has underlying physical health issues, that specialist referral is made to an Endocrinologist, neurologist, immunologist. Something needs to be done about this very urgently to stop mental health patients from being harmed. I shall post further example of the known effects of Aripiprazole which I doubt was ever informed in the circumstances. It is only right that patients are properly informed.

https://revelationsuk.com/2025/10/29/outdated-practices/

Off-Label Aripiprazole for Antipsychotic-Induced Hyperprolactinaemia: Clinical Judgement, Endocrine Risk and the Evolving Legal Standard of Care

The use of adjunctive aripiprazole to treat antipsychotic-induced hyperprolactinaemia has become an increasingly accepted off-label strategy within psychiatric practice. Randomised trials and systematic reviews demonstrate that low-dose aripiprazole can reduce serum prolactin concentrations in many patients receiving prolactin-raising antipsychotics. Yet clinical efficacy alone does not determine whether prescribing is appropriate.

Where treatment is off-label, the patient remains prescribed a long-acting depot antipsychotic, and there is evidence of multiple endocrine or metabolic abnormalities, the clinician’s responsibilities extend well beyond correcting a biochemical abnormality. The decision engages principles of clinical governance, informed consent, multidisciplinary care and, ultimately, the legal standard of care.

The medico-legal question is therefore not simply whether aripiprazole lowers prolactin. It is whether introducing a second dopamine-modulating medicine represents a reasonable, proportionate and defensible clinical response in the individual patient.

Off-Label Prescribing and the GMC: Professional Responsibilities

The General Medical Council’s Good practice in prescribing and managing medicines and devices recognises that prescribing outside a medicine’s licence may be appropriate. However, the guidance also makes clear that such prescribing carries enhanced professional responsibilities.

The prescriber should be satisfied that:

  • sufficient evidence or clinical experience supports the proposed treatment;
  • licensed alternatives have been properly considered;
  • the anticipated benefits outweigh foreseeable risks;
  • the patient is informed that treatment is being used outside its licensed indication where discussion is practicable;
  • material risks and reasonable alternatives are discussed;
  • the clinical reasoning is documented; and
  • appropriate monitoring arrangements are established.

These obligations become particularly important when the additional medication is not treating the primary psychiatric illness but is instead intended to mitigate an adverse effect of another prescribed psychotropic medicine.

NICE and the Royal College of Psychiatrists: Treat the Whole Patient

NICE guidance on psychosis, schizophrenia and medicines optimisation consistently promotes careful review of antipsychotic adverse effects rather than reflexively adding further medication. Hyperprolactinaemia should prompt reassessment of the overall treatment strategy, consideration of dose reduction where feasible, or switching to a prolactin-sparing antipsychotic if clinically appropriate.

Similarly, the Royal College of Psychiatrists has repeatedly emphasised that people with severe mental illness experience disproportionate rates of obesity, diabetes, cardiovascular disease, endocrine dysfunction and premature mortality. The College advocates parity of esteem between physical and mental healthcare, requiring psychiatrists to investigate physical illness with the same rigour expected in any other medical specialty.

Persistent hyperprolactinaemia accompanied by type 2 diabetes mellitus, obesity, hypogonadism, osteoporosis or other endocrine abnormalities should therefore trigger consideration of broader endocrine pathology rather than being viewed solely as a medication side effect.

Depot Antipsychotics Create a Higher-Risk Pharmacological Environment

The addition of aripiprazole is particularly complex where the patient remains prescribed depot antipsychotic injections.

Depot preparations cannot be rapidly withdrawn if clinically significant adverse effects develop. Dopamine receptor blockade continues for weeks after administration, substantially reducing therapeutic flexibility.

If adjunctive aripiprazole precipitates akathisia, agitation, insomnia or behavioural deterioration, clinicians cannot immediately remove the underlying pharmacological interaction. Consequently, the threshold for introducing additional dopamine-modulating medication should arguably be higher than in patients treated solely with oral antipsychotics.

Akathisia Is Not a Minor Adverse Effect

Aripiprazole is generally well tolerated, but akathisia remains one of its most clinically significant adverse effects.

Patients frequently describe overwhelming inner restlessness, profound anxiety, inability to remain still, agitation and severe psychological distress. These symptoms can be mistaken for worsening psychosis, anxiety disorders or behavioural disturbance, potentially resulting in further inappropriate prescribing.

The literature has also associated severe untreated akathisia with treatment discontinuation, self-harm and suicidal ideation in some patients.

Where aripiprazole has been prescribed solely to lower prolactin concentrations, the emergence of akathisia fundamentally alters the balance between therapeutic benefit and clinical risk.

Appropriate management should include urgent clinical review, consideration of dose reduction or discontinuation, reassessment of the antipsychotic regimen, symptomatic treatment where indicated, and close follow-up until symptoms resolve.

Multiple Endocrine Abnormalities Should Prompt Endocrinology Referral

The presence of hyperprolactinaemia together with type 2 diabetes mellitus or other endocrine abnormalities should prompt clinicians to ask a broader diagnostic question.

Is the patient experiencing a medication side effect alone, or does the presentation reflect wider endocrine disease requiring specialist investigation?

Potential differential diagnoses include pituitary pathology, hypogonadism, thyroid disease, adrenal disorders, metabolic syndrome and osteoporosis.

Adding aripiprazole may improve one biochemical parameter while delaying diagnosis of another clinically significant disorder.

Referral to a consultant endocrinologist should therefore be strongly considered where endocrine dysfunction extends beyond isolated hyperprolactinaemia, where symptoms remain unexplained, or where long-term complications require specialist assessment.

The Legal Framework: From Bolam to Montgomery

The legal analysis of these prescribing decisions has evolved significantly over recent decades.

Bolam v Friern Hospital Management Committee [1957]

The Bolam principle established that a clinician is not negligent simply because another clinician would have acted differently, provided the decision accords with a responsible body of professional opinion.

Historically, this afforded considerable protection to prescribing decisions supported by accepted clinical practice.

However, modern medical negligence law has moved well beyond Bolam alone.

Bolitho v City and Hackney Health Authority [1998]

The House of Lords refined the Bolam principle by holding that professional opinion itself must withstand logical analysis.

Courts are not obliged to accept expert evidence merely because other clinicians support it. The opinion must demonstrate coherent reasoning and appropriately balance risks against benefits.

In practical terms, this means that merely stating “adjunctive aripiprazole is accepted practice” may be insufficient if inadequate consideration was given to endocrine disease, alternative treatment options, foreseeable adverse effects or the patient’s individual circumstances.

Montgomery v Lanarkshire Health Board [2015]

The Supreme Court fundamentally reshaped informed consent.

Clinicians are now under a legal duty to ensure that patients are informed of:

  • material risks associated with proposed treatment;
  • reasonable alternative treatment options; and
  • the option of declining treatment altogether where appropriate.

A risk is material if a reasonable person in the patient’s position would likely attach significance to it, or if the clinician knows, or should reasonably know that the particular patient would likely consider it significant.

Applied to adjunctive aripiprazole, this means patients should ordinarily be informed about:

  • the off-label nature of treatment;
  • the possibility of akathisia, agitation and insomnia;
  • the possibility that treatment may not adequately resolve symptoms;
  • alternatives such as dose reduction, switching antipsychotics where clinically feasible, observation, or referral for endocrine assessment;
  • the uncertainties associated with adding another psychotropic medicine.

Failure to discuss these matters may expose clinicians to criticism even where prescribing itself was pharmacologically reasonable.

Documentation: The Clinician’s Strongest Defence

In medico-legal practice, contemporaneous documentation frequently determines whether a prescribing decision can be defended.

The medical record should clearly demonstrate:

  • why adjunctive aripiprazole was preferred over alternative strategies;
  • evidence supporting off-label prescribing;
  • informed consent discussions;
  • endocrine and metabolic assessment;
  • monitoring plans;
  • review arrangements;
  • contingency planning should adverse effects emerge.

Documentation should reflect a process of clinical reasoning rather than simply recording a prescribing decision.

Conclusion

Adjunctive aripiprazole remains a legitimate therapeutic option for selected patients with antipsychotic-induced hyperprolactinaemia. However, legitimacy does not eliminate professional responsibility.

Current GMC guidance, NICE recommendations and Royal College of Psychiatrists policy all point towards careful assessment, shared decision-making, systematic physical health monitoring and multidisciplinary management.

The legal authorities of Bolam, Bolitho and Montgomery reinforce these professional duties by requiring that prescribing decisions are supported by logical clinical reasoning, informed by responsible practice, and accompanied by meaningful patient involvement.

Where a patient receiving depot antipsychotic treatment develops persistent hyperprolactinaemia alongside diabetes mellitus or other endocrine abnormalities, the question should not simply be how to suppress prolactin. The more important question is whether the patient requires comprehensive endocrine investigation before additional psychotropic medication is introduced.

In many such cases, early referral to a consultant endocrinologist, combined with a multidisciplinary review of the antipsychotic regimen, is likely to represent the most clinically robust and the most legally defensible course of action.

This is why a precision based approach to psychiatry is necessary and not the antiquated and discredited system known as psychogenics, which far more resemble a belief system than any modern scientific evidence based medicine system. 

The psychogenic ‘symptom’ based approach to diagnosis is more a relic of the early 20th century than an evidence based medicine model and in the main health trusts still relying on this are likely lazy and dogmatic and have failed to keep up with neurological research and appropriate training of staff.  Apart from the obvious distress this causes to patients and their loved ones it represents a retrograde attitude to advancing psychiatric and neurological models.  Patents often spend years misdiagnosed and consequently incorrectly treated and more often than not detained in the forensic legal system that also sustains this intellectual bankruptcy in the medical professions. 

The underlying motivation of psychogenic psychiatry is isolation, deprivation of liberty and containment of what is often seem as more of a legal problem than one involving innocent victims of a medical pathology. 

There are several plausible and increasingly studied links between polyendocrine disorders and dysfunctional signaling in the mesolimbic system, particularly involving dopamine, stress hormones, immune signaling, and metabolic hormones. But the relationship is complex and usually indirect rather than a single unified disease mechanism.

The mesolimbic system (especially the VTA → nucleus accumbens dopamine pathway) regulates motivation, reward salience, reinforcement learning, mood, and aspects of energy regulation. Dysregulation in this circuit is implicated in depression, addiction, anhedonia, compulsive behaviours, schizophrenia-spectrum symptoms, and altered motivational states. 

Several endocrine systems feed directly into this circuitry:

1.     Cortisol / HPA axis

2.     Thyroid hormones

3.     Insulin and leptin

4.     Sex steroids

5.     Inflammatory cytokines

6.     Orexin and ghrelin signaling

7.     Prolactin-dopamine feedback loops

So when multiple endocrine systems become dysregulated simultaneously, as in polyendocrine syndromes mesolimbic signaling can adversely be affected.

A few examples of Autoimmune polyendocrine syndromes includes conditions like autoimmune polyendocrine syndrome (APS) often involve chronic inflammation, adrenal dysfunction, thyroid disease, diabetes, or gonadal hormone abnormalities. Cytokines and glucocorticoid instability can alter dopamine neuron firing and reward processing. Chronic inflammatory states are increasingly associated with reduced dopaminergic motivation signaling and anhedonia. 

Thyroid dysfunction.  Hypothyroidism can blunt dopaminergic tone and produce apathy, reduced motivation, depression and cognitive slowing

Hyperthyroidism can produce anxiety, agitation, reward/salience dysregulation and sometimes psychosis-like symptoms

These effects likely involve mesocorticolimbic dopamine modulation. The mesolimbic pathway is highly sensitive to glucocorticoids. Chronic excess cortisol can alter reward salience and stress responsivity, while adrenal insufficiency can impair motivation and emotional regulation. Stress-hormone modulation of VTA dopamine neurons is well established. 

Diabetes and insulin resistance influences. Insulin receptors are expressed in mesolimbic dopamine regions. Impaired insulin signaling can alter reward valuation, food motivation, impulsivity, and dopaminergic transmission. This is one reason metabolic disease and compulsive eating/addiction phenotypes overlap neurobiologically. 

Prolactin and dopamine.  There is a direct endocrine-dopamine loop. Dopamine inhibits prolactin release through D2 receptor signaling. Disorders involving prolactin, pituitary dysfunction, or dopamine blockade can therefore affect motivation, libido, affect, and reward processing. 

There is also an emerging idea that some syndromes that appear “psychiatric,” “metabolic,” and “endocrine” at the same time may involve shared network dysfunction between hypothalamic regulation, immune signaling, salience/reward circuitry and autonomic regulation

That overlap is especially discussed in chronic stress disorders, obesity/metabolic syndrome, inflammatory illnesses, chronic pain syndromes and some neuroimmune conditions


A mesolimbic abnormality would not usually be considered the primary cause of a polyendocrine disorder in mainstream medicine.  More commonly endocrine dysfunction alters mesolimbic signaling, or both are affected by a third process (autoimmune, inflammatory, genetic, developmental, or stress-related).

So the association is biologically credible and supported by growing evidence, but it is not yet a fully unified or clinically standardized framework.

How Medicine Works and When It Doesn’t: Learning Who to Trust to Get and Stay Healthy Hardcover – 24 Jan. 2023 
by  F Perry Wilson  (Author)
4.5  4.5 out of 5 stars       33 ratings
See all formats and editions
Blending personal anecdotes with hard science, an accomplished physician, researcher, and science communicator gives you the tools to avoid medical misinformation and take control of your health​ “A brilliant step toward patients and physicians alike reclaiming a sense of confidence in a system that often feels overwhelming and mismanaged” (Gabby Bernstein, #1 New York Times bestselling author of The Universe Has Your Back).

We live in an age of medical miracles. Never in the history of humankind has so much talent and energy been harnessed to cure disease. So why does it feel like it’s getting harder to live our healthiest lives? Why does it seem like “experts” can’t agree on anything, and why do our interactions with medical professionals feel less personal, less honest, and less impactful than ever? 

Through stories from his own practice and historical case studies, Dr. F. Perry Wilson, a physician and researcher from the Yale School of Medicine, explains how and why the doctor-patient relationship has eroded in recent years and illuminates how profit-driven companies–from big Pharma to healthcare corporations–have corrupted what should have been medicine’s golden age. By clarifying the realities of the medical field today, Dr. Wilson gives readers the tools they need to make informed decisions, from evaluating the validity of medical information online to helping caregivers advocate for their loved ones, in the doctor’s office and with the insurance company. 

Dr. Wilson wants readers to understand medicine and medical science the way he does: as an imperfect and often frustrating field, but still the best option for getting well. To restore trust between patients, doctors, medicine, and science, we need to be honest, we need to know how to spot misinformation, and we need to avoid letting skepticism ferment into cynicism. For it is only by redefining what “good.

Maria Cristina Patru1 and David H. Reser 2*
1Department of Psychiatry, Hôpitaux Universitaires de Genève, Geneve Switzerland, 2 Department of Physiology, Monash
University, Melbourne, Australia
Edited by:
Bernat Kocsis,
Harvard Medical School, USA
Reviewed by:
Sabina Berretta,
McLean Hospital, USA
Ami Citri,
The Hebrew University, Israel
*Correspondence:
David Reser
david.reser@monash.edu
Specialty section:
This article was submitted to
Schizophrenia,
a section of the journal
Frontiers in Psychiatry
Received: 23 July 2015
Accepted: 26 October 2015
Published: 09 November 2015
Citation:
Patru MC and Reser DH (2015)
A New Perspective on Delusional
States – Evidence for
Claustrum Involvement.

Front. Psychiatry 6:158.
doi: 10.3389/fpsyt.2015.00158

“Delusions are a hallmark positive symptom of schizophrenia, although they are also
associated with a wide variety of other psychiatric and neurological disorders.

The heterogeneity of clinical presentation and underlying disease, along with a lack of experimental
animal models, make delusions exceptionally difficult to study in isolation, either in
schizophrenia or other diseases. To date, no detailed studies have focused specifically on
the neural mechanisms of delusion, although some studies have reported characteristic
activation of specific brain areas or networks associated with them. Here, we present a
novel hypothesis and extant supporting evidence implicating the claustrum, a relatively
poorly understood forebrain nucleus, as a potential common center for delusional states.”

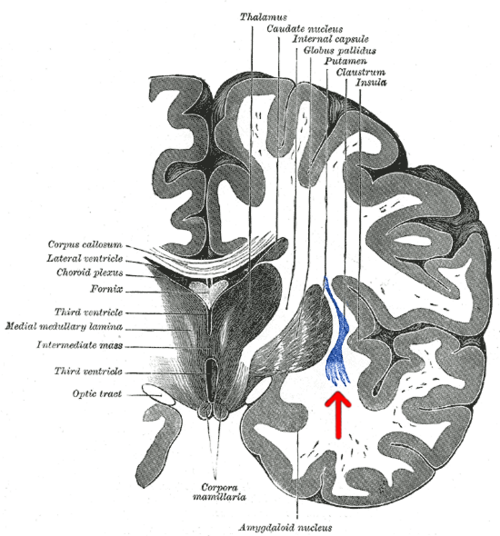
Elizabeth’s scan shows a lesion in precisely that area of the brain (marked in blue with red arrow) which needs to be properly identified.  See also page three of the PDF paper.

This is directly in the meso-limbic pathway and is associated with delusional behaviour in what some people are still calling schizophrenia.   

If you look at page 3 of this paper you will see the brain pictured in coronal, sagittal and horizontal view and the arrows triangulate to where the image/lesion appears in the right hemisphere of her brain on the scan at position 7/24 of the coronal image from the MRI.   

This urgently needs looking at by a neurologist and reference needs to be made to this paper.

Whilst commencing to write this blog Elizabeth has just called. She said yesterday that she spent six hours in seclusion whilst being rapidly tranquilised on Xmas Day.

Despite this, Elizabeth did not sound too bad during her supervised phone call. She spoke of escape. By this she clearly said that she escapes in her mind ie dissociation - this is a sign of PTSD for which Elizabeth has never had any treatment for under NHS. Also she has never had underlying pathological tests until I have had to point out the results of the private scan and observations by independent specialists and experts.

With an appointment on the 3 January with a Neurologist that had previously been flatly refused I really do hope that once and for all her whole treatment will be reviewed based upon the findings which clearly indicate the above.

It has been a nightmare to even try to get certain doctors to acknowledge let alone look into something that has been clearly stated in the files going back to 2009. This could all indicate why the treatment has not worked for so many years.

I am very unhappy at the current punishment of having the phone taken away for a trial period. This has already been tried before. I see this as bullying aimed directly at me because I am the one being blamed for the ‘episodes’ that look like fits never seen before even though many of these take place when I am not around. The necessity the MDT believes to be right is completely wrong and has not achieved anything before at Ash Villa except mistrust and upset and nothing is being done in line with the law and correct procedures and now these same restrictions incorporating Xmas is yet again being “tried”.

I hope to put an end to this bullying once and for all as that is how we see it. I am not going to sit back and do nothing whilst this punishment continues for years and years on end as I believe the whole environment of a noisy acute ward to be completely wrong and the whole approach of punishment also.

This is punishment not care. Punishment to stop my daughter from going out to the shop in the hospital grounds, punishment from stopping her listening to her music on her phone by keeping it locked away. What is this achieving?  NOTHING but resentment an mistrust and this has been ongoing for one month now with no end in sight.  

“Treat people as individuals and uphold their dignity and to do this you must treat people with kindness, respect and compassion and respect and uphold people’s human rights, challenge poor practice and discriminatory attitudes and behaviour relating to their care.

“Act with honesty and integrity at all times, treating people fairly without discrimination, bullying or harassment.  Keep to the laws of the country in which you are practising. Never allow someone’s complaint to affect the care that is provided to them.”